Safe Transfusion · Iron Chelation · Bone Marrow Transplant · Gene Therapy · Lifelong Follow-Up
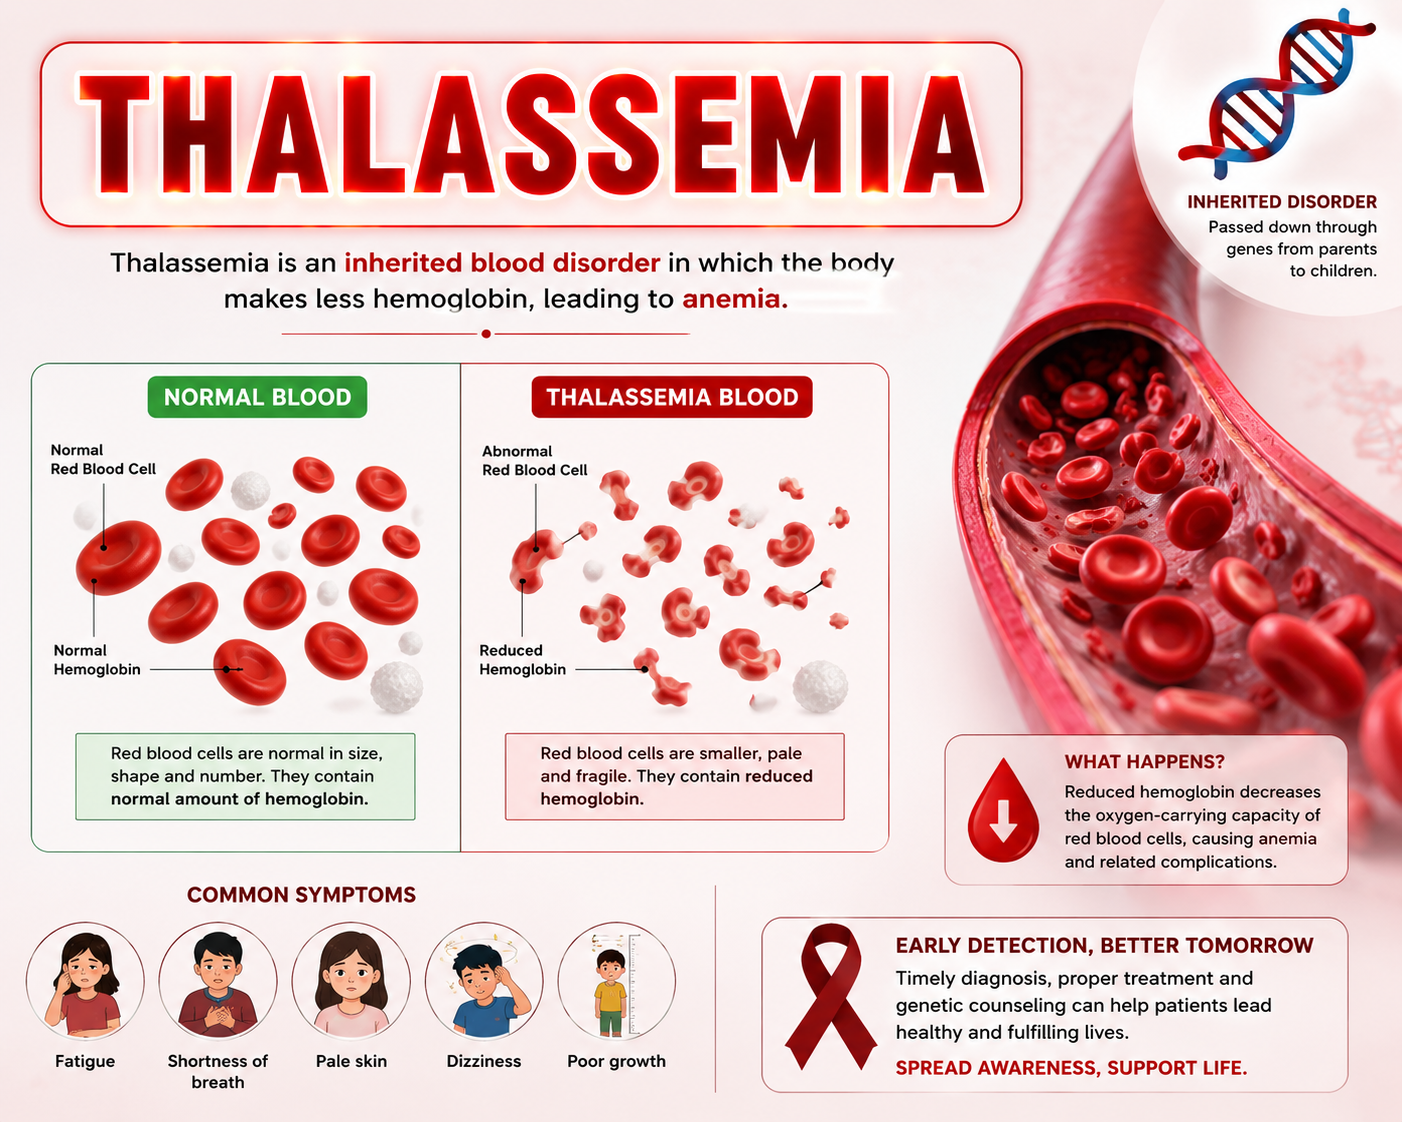
Thalassemia is a group of inherited blood disorders in which the body produces an abnormal form or inadequate amount of haemoglobin — the protein in red blood cells that carries oxygen throughout the body. The result is chronic anaemia, fatigue, organ damage and, in severe forms, lifelong dependence on blood transfusions.
India is recognised as one of the world's leading destinations for thalassemia care, offering safe leucodepleted transfusions, oral iron chelation, allogeneic bone marrow transplantation and emerging gene therapy at JCI/NABH accredited centres — at a cost 60–80% lower than the USA, UK or Europe. Major Indian transplant centres achieve overall survival rates of 90–95% in matched sibling donor transplants for thalassemia major.
Haemoglobin is made of two protein chains — alpha-globin and beta-globin. Thalassemia occurs when a genetic mutation reduces or stops production of one of these chains. The imbalance causes red blood cells to break down prematurely (haemolysis), leading to anaemia and complications affecting the bones, spleen, liver, heart and endocrine organs.
Thalassemia is an autosomal recessive disorder, meaning a child must inherit a defective gene from both parents to develop the disease. If only one parent passes on the gene, the child becomes a carrier (thalassemia minor or trait) — usually asymptomatic but able to pass the gene to future generations.
Caused by mutations or deletions in the alpha-globin genes (HBA1 and HBA2 on chromosome 16). Severity depends on how many of the four alpha genes are affected: silent carrier (1 gene), alpha thalassemia trait (2 genes), Haemoglobin H disease (3 genes), and Hydrops fetalis / Hb Bart's (4 genes — usually fatal in utero).
Caused by mutations in the beta-globin gene (HBB on chromosome 11). Classified clinically as: thalassemia minor (trait), thalassemia intermedia (non-transfusion-dependent but symptomatic), and thalassemia major (Cooley's anaemia — severe, transfusion-dependent from infancy).
Common in South and Southeast Asia, ranging from mild to severe phenotype depending on the specific mutations inherited.
Rarer forms with variable clinical presentations, often milder than classical beta thalassemia.
Symptoms vary widely with the type and severity of the disease. Children with thalassemia major usually develop symptoms within the first 6–24 months of life, while milder forms may not be diagnosed until later in childhood or adulthood.
Early and accurate diagnosis is essential for proper management and family counselling. India's leading haematology and genetic centres offer the full spectrum of investigations:
Treatment depends on type and severity, age, and presence of complications. Indian centres offer the complete spectrum of modern care.
For thalassemia major, regular packed red blood cell transfusions every 2–4 weeks are the foundation of care. The goal is to maintain pre-transfusion haemoglobin between 9.5 and 10.5 g/dL to suppress ineffective erythropoiesis and allow normal growth. India's top hospitals use leucodepleted, phenotype-matched and antigen-screened blood to reduce reactions and alloimmunisation.
Each unit of transfused blood deposits about 200–250 mg of iron in the body. Without removal, iron accumulates and damages the heart, liver and endocrine organs.
Allogeneic haematopoietic stem cell transplantation (HSCT) is the only established cure for thalassemia major. It replaces the patient's defective bone marrow with healthy stem cells from a matched donor. Best results are achieved in children under 14 years of age, before significant iron overload and organ damage.
India is a global hub for BMT in thalassemia, with leading centres performing 500+ transplants per year.
A revolutionary approach for transfusion-dependent thalassemia. The patient's own stem cells are collected, genetically modified to produce normal beta-globin (using lentiviral vectors or CRISPR), and reinfused after conditioning chemotherapy — eliminating the need for a donor. Betibeglogene autotemcel (Zynteglo) and exagamglogene autotemcel (Casgevy, CRISPR-based) have been approved internationally, and select Indian centres now offer gene therapy through clinical trial and tertiary-centre pathways.
Splenectomy may be considered when transfusion requirements rise due to hypersplenism. Other supportive measures include vaccination against encapsulated bacteria (pneumococcus, meningococcus, Haemophilus), management of endocrine complications, calcium and vitamin D for bone health, cardiac monitoring, and treatment of viral hepatitis when present.
India performs more allogeneic BMTs for thalassemia than any country outside the US and Italy.
MD/DM-qualified specialists trained at AIIMS, CMC Vellore, Tata Memorial, USA, UK and Italy.
Comprehensive treatment including BMT at a fraction of Western costs — without compromising quality.
Immediate consultation, HLA typing and transplant scheduling within weeks of arrival.
* Costs vary by donor type, conditioning regimen, hospital stay and post-transplant complications. Contact Satyug Healthcare for a personalised estimate.
Outcomes have improved dramatically over the past three decades. With optimal transfusion and chelation therapy, life expectancy for thalassemia major patients now extends well into the 4th and 5th decades. For children who undergo successful BMT before 14 years of age with a matched sibling donor, overall survival reaches 90–95% and the majority enjoy a thalassemia-free, transfusion-free life. Gene therapy is poised to expand cure options to patients without a suitable donor. Modern thalassemia care today offers patients a near-normal quality of life.
Travelling abroad for thalassemia care — particularly bone marrow transplantation — needs careful coordination. Satyug Healthcare makes this journey smooth and stress-free.
Send CBC, HPLC, ferritin, MRI T2*, HLA typing — get written opinion from a leading haematologist.
Consultations with two or more BMT specialists so you can choose who you trust most.
BLK-Max, Apollo, Medanta, Fortis Memorial, Rainbow Children's, Amrita, Max Saket, Manipal Dwarka, Artemis, CMC Vellore, Tata Memorial.
Expedited medical visa invitation letter for patient and accompanying family members.
Airport pickup, long-stay accommodation, donor workup, transplant scheduling and follow-ups.
English, Arabic, Russian, French, Bengali — no communication barriers.
HLA typing of siblings and access to international unrelated donor registries when needed.
Video consultations to monitor engraftment, chimerism, immunosuppression and complications.
Q1. Can thalassemia be cured?
Yes. Allogeneic bone marrow / stem cell transplantation is currently the only established cure for thalassemia major, offering disease-free survival of 85–90% in children with a matched sibling donor. Gene therapy is an emerging curative option for patients without a suitable donor. For thalassemia minor, no cure is needed as it is essentially asymptomatic.
Q2. What is the best age for bone marrow transplant?
The ideal age is between 2 and 14 years, before significant iron overload causes organ damage. Younger, low-risk patients (Pesaro Class I–II) have the best outcomes. BMT can still be considered in older patients in carefully selected cases.
Q3. What if my child does not have a matched sibling donor?
Several options exist: international unrelated donor registries (MUD), half-matched family donor (haploidentical BMT with post-Tx cyclophosphamide), umbilical cord blood transplantation, or gene therapy. India's top centres now offer haploidentical BMT routinely, meaning nearly every patient can find a donor.
Q4. What documents do I need to share?
Send: (1) recent CBC and peripheral smear, (2) HPLC / electrophoresis report, (3) serum ferritin and iron studies, (4) cardiac and liver MRI T2* if available, (5) HLA typing of patient and siblings if done, (6) hospital admission/discharge summaries, (7) viral marker reports (HBV, HCV, HIV), (8) current medication list. WhatsApp or email — opinion within 24–48 hours.
Q5. How long does the BMT process take in India?
2–4 weeks for pre-transplant workup and donor preparation, 4–6 weeks of hospital admission for conditioning and transplant, then 2–3 months of close outpatient follow-up. Most international families plan a 4–6 month stay. Affordable accommodation near hospitals is available for family.
Get a free written medical opinion from a leading haematologist or transplant specialist in India within 24–48 hours — at no obligation.
📞 +91-8860606766 | +91-9910655125
✉️ query@satyughealthcare.com · 💬 WhatsApp 24/7